
Unbiased headlines. Facts, not spin.
Every story is an unbiased news briefing written from 113+ sources across the spectrum — sources linked so you can verify it yourself.
 health
Notable (5/10)
Event date: September 22, 2026
Four FDA-Cleared Blood Tests and a New Protein Clue Mark a Shift in Alzheimer's Diagnosis
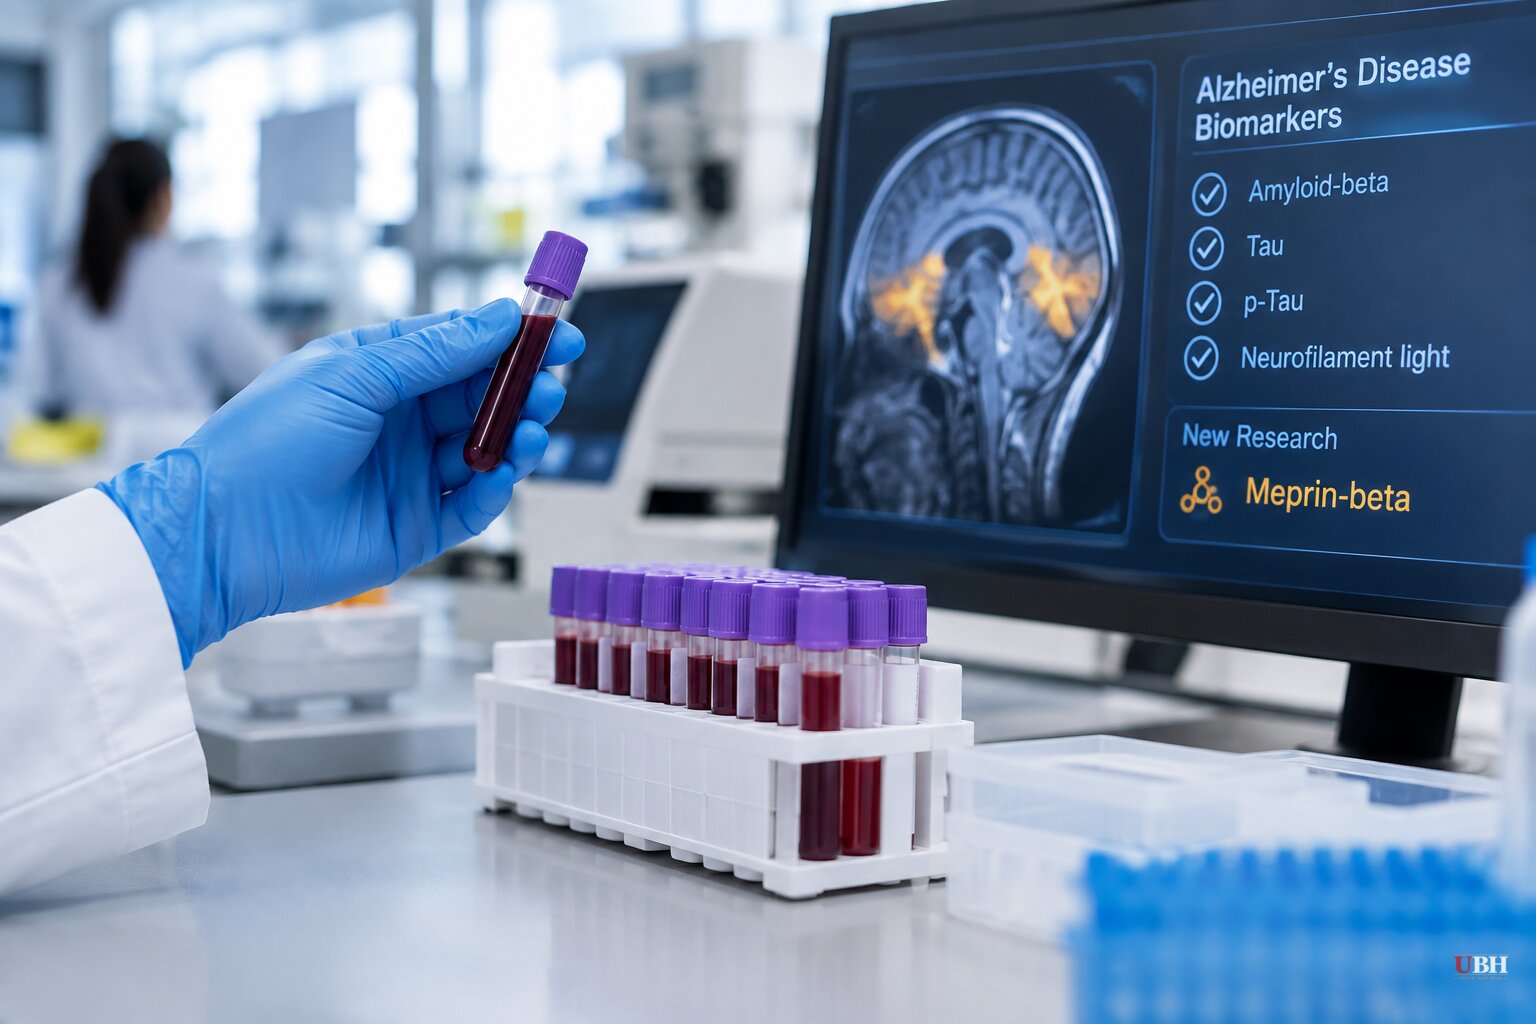
Diagnosing Alzheimer's disease used to mean waiting for an autopsy. Now doctors have a blood draw.
Four blood tests have been cleared by the U.S. Food and Drug Administration to detect early signs of Alzheimer's, according to TIME. The first, made by Fujirebio, was cleared in May 2025 and measures a ratio of beta amyloid and tau proteins, but it requires specialized lab equipment that limits where it can be run. The second, from Roche, was cleared in October 2025 and is the first test primary care doctors can prescribe to rule out the disease.
Two more tests were cleared in August 2026. One is PrecivityAD2, made by C2N Diagnostics, which uses mass spectrometry to generate a probability score for amyloid plaques and is available through major commercial labs, not just specialized centers. Dr. Eric Reiman, CEO emeritus and lead researcher at the Banner Alzheimer's Institute in Phoenix, told TIME the moment marks a shift toward personalized care similar to oncology: "We're going to start personalizing Alzheimer's care similar to cancer, where we can inform diagnosis, prognosis, and staging to further inform disease severity."
A separate validation study published in the June 2026 issue of Alzheimer's & Dementia, reported by Medical Dialogues, tested a plasma ratio of p-tau217 and amyloid beta 1-42 across 499 adults ages 52 to 93 pulled from five independent research cohorts, including BioFINDER-2 and the Wisconsin Registry for Alzheimer's Prevention. Using amyloid PET imaging and spinal fluid tests as the reference standard, the ratio correctly identified nearly 98% of patients who actually had amyloid pathology, according to the study.
A New Protein in the Mix
Blood and spinal fluid tests already look for amyloid and tau. Now researchers are adding a third target: meprin-beta.
A study published in Alzheimer's Research & Therapy and reported by Newsweek found that the active form of this enzyme is elevated in both brain tissue and cerebrospinal fluid of Alzheimer's patients, and that the elevation tracks with disease progression rather than showing up in the earliest stages. Researchers examined frontal cortex tissue staged using the Braak system, a standard measure of how far Alzheimer's pathology has spread, and found rising levels of active meprin-beta and its genetic template, MEP1B messenger RNA, in intermediate and advanced disease.
Dr. Steven Chance, founder and chief scientific officer at Oxford Brain Diagnostics, told Newsweek the finding "adds an important piece to our understanding of the complex biology behind Alzheimer's disease," but cautioned that fluid biomarkers alone don't reveal how early the brain is affected or how its structure changes over time. Pairing biomarker data with brain imaging is the next logical step.
The Treatment Side Is Still Limited
Earlier, cheaper diagnosis only matters if there's something to do with the information. That's where the picture gets more complicated.
Amyloid-targeting antibody drugs, approved in recent years, were the first therapies shown to slow clinical decline in some early-stage patients, according to an industry perspective published on Pharmaphorum. But the same piece, written from the standpoint of a company developing a next-generation antibody, acknowledges the current drugs come with "modest average treatment effects," require ongoing infusions and imaging monitoring, and carry a real risk of amyloid-related imaging abnormalities, brain swelling or bleeding tied to the treatment itself.
That's a legitimate concern. Patients on these drugs need regular MRI scans to catch ARIA before it becomes dangerous, and the benefit for the average patient is measured in a slower rate of decline, not a cure or reversal. Pharmaphorum's argument is that the field is now trying to target only the most toxic soluble amyloid particles rather than broadly clearing plaque, in hopes of keeping the benefit while cutting the risk. That approach is still in clinical development and unproven at scale.
Dr. Jorge G. Ruiz, writing for Memorial Healthcare System in southfloridahospitalnews, put it plainly: anti-amyloid infusion therapies "are not a cure," but for carefully selected early-stage patients they have been shown to slow progression and help maintain independence longer.
Where the Money Is Going
The research pipeline behind all of this got a boost this week. The Cleveland Alzheimer's Disease Research Center received a five-year NIH grant renewal worth an expected $21.1 million, running from 2026 through 2031, according to Cleveland Clinic. The center, the only one of its kind in Ohio, is a partnership between Cleveland Clinic, Case Western Reserve University, the VA Northeast Ohio Health Care System, MetroHealth and University Hospitals. It was established in 2019 and is directed by Dr. Jagan Pillai, who also runs Cleveland Clinic's Center for Brain Health.
Pillai told Cleveland Clinic the goal is to build a research cohort that tracks patients over time to identify "medical, biological, cognitive and functional predictors" of how fast the disease progresses in different people, something current biomarker tests can flag but not fully explain.
Cheaper, faster blood tests can tell a patient they have amyloid plaques building up years before symptoms appear. What no test yet answers is how fast that person's decline will actually happen, or whether treating it early with today's antibody drugs changes that trajectory meaningfully enough to justify the cost, the infusions, and the ARIA risk. The Cleveland grant and the meprin-beta research are both aimed at closing that gap. Neither has closed it yet.
Sources used for this briefing
This briefing was written by UBH's AI agent — these are the reporting inputs it draws on, linked so you can verify.


