
Unbiased headlines. Facts, not spin.
Unbiased Headlines is an independently owned news organization. We bring you the facts, not opinions, written fresh from 110+ named sources. Sources linked so you can verify it yourself.
 health
Notable (6/10)
Event date: November 3, 2026 ·
TAVR Cut Death and Heart Failure Events in Moderate Aortic Stenosis Patients With Risk Features, Edwards-Funded Trial Finds
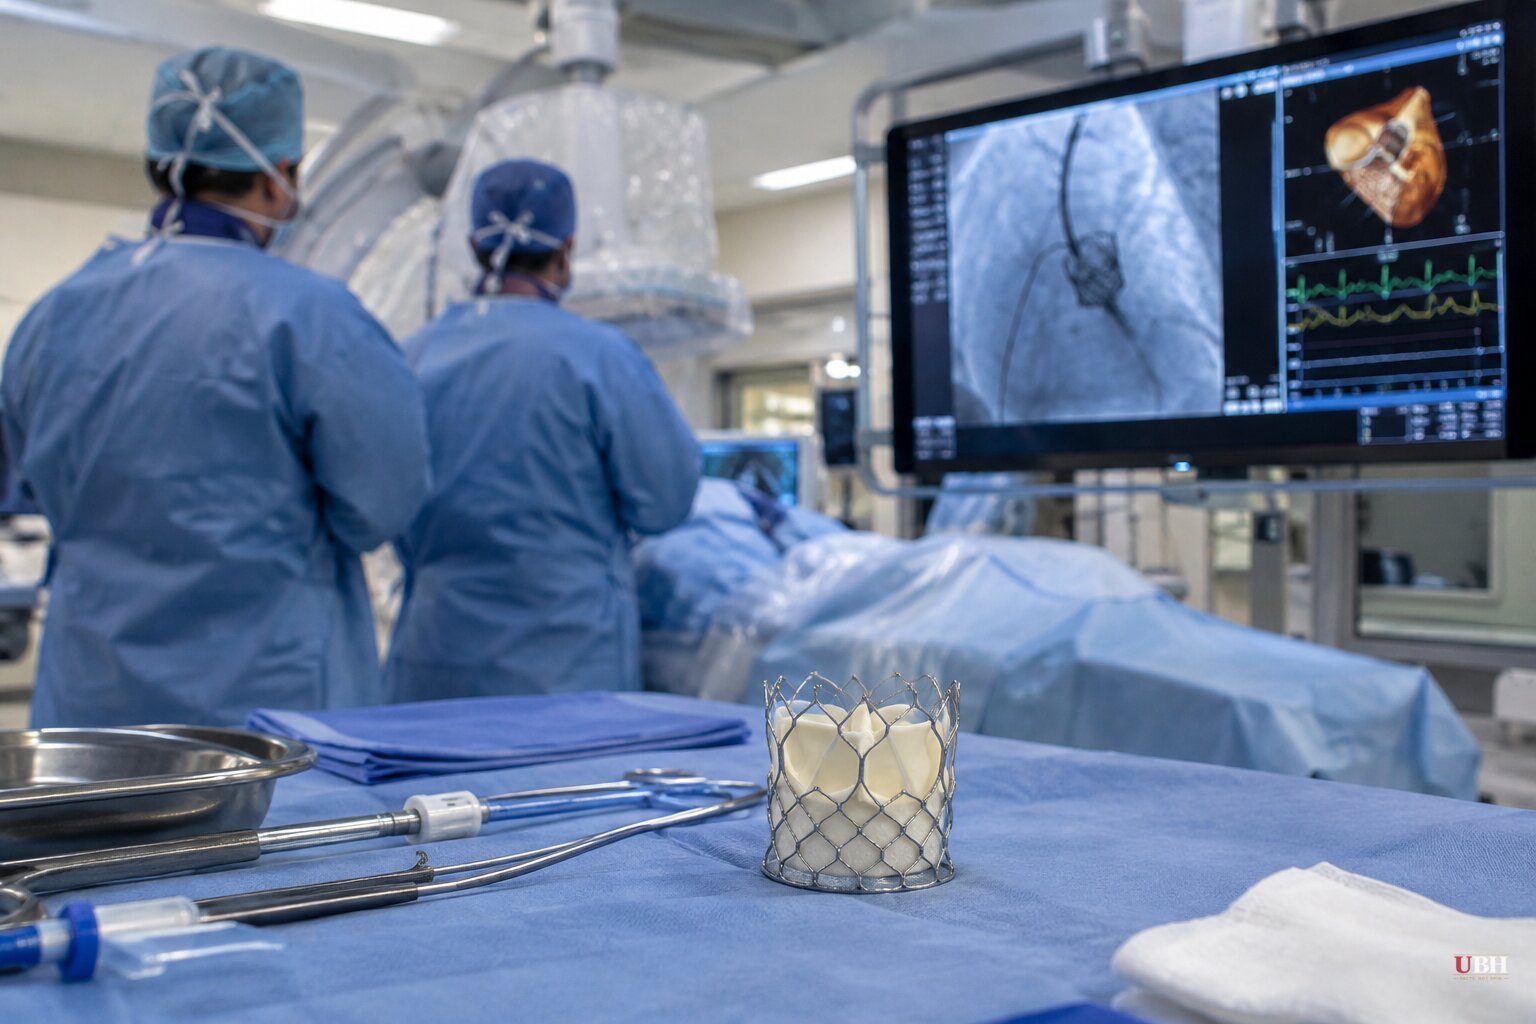
A randomized trial funded by the valve's manufacturer says some patients with moderate aortic stenosis do better if they get a new valve now rather than waiting for the disease to turn severe.
The PROGRESS trial was presented Monday, Nov. 2, at the Transcatheter Cardiovascular Therapeutics (TCT) 2026 meeting in San Diego. It was published simultaneously in the New England Journal of Medicine.
What the trial found
Investigators randomized 744 patients at 74 centers in the U.S., Japan, Australia, Europe and Canada. Enrollment ran from October 2021 to January 2024. Of those patients, 373 were assigned to transcatheter aortic valve replacement (TAVR) and 371 to clinical surveillance, with valve replacement available when indicated.
All had moderate aortic stenosis and at least one at-risk feature. The list included symptoms of at least NYHA Class II, a reduced ejection fraction, diastolic dysfunction, low stroke volume, recent atrial fibrillation, elevated NT-proBNP or a high CT calcium score.
The average patient was 78 years old. 39.1% were women, and 45.6% were at low surgical risk.
At two years, death or a heart failure event had occurred in 16.7% of the TAVR group and 23.9% of the surveillance group. The hazard ratio was 0.67 (95% CI 0.48-0.93, P=0.02 for superiority). The risk difference was 7.2 percentage points.
Heart failure hospitalizations were cut roughly in half: 26 patients in the TAVR group (7.4%) versus 52 in the surveillance group (14.9%).
A secondary endpoint of death, stroke or heart failure hospitalization came in at 17.7% for TAVR and 23.3% for surveillance. And 39% of TAVR patients were alive with a gain of at least 10 points on the Kansas City Cardiomyopathy Questionnaire, versus 23.2% of surveillance patients.
Safety and the surveillance arm
The 30-day safety endpoint covered death, stroke, life-threatening bleeding, stage 4 kidney injury, device- or procedure-related hospitalization and reintervention for valve dysfunction. It occurred in 5.9% of TAVR patients. The prespecified performance goal was 13.7%. Most events were hospitalizations for device- or procedure-related complications, at 5.6%.
That safety result was measured against a preset benchmark, not against the surveillance group.
The patients who waited did not stay put. In the surveillance arm, 204 patients underwent delayed aortic valve replacement during follow-up. About 80% of them had progressed to severe stenosis by the time of the procedure.
"This disease progressed faster than [we] expected," said lead investigator Philippe Généreux of Morristown Medical Center in New Jersey. "You need to follow these patients. You cannot abandon them."
The investigators' read
Généreux said the data point toward earlier referral. "Moderate AS is not benign," he said. "Rather than waiting for progression to severe AS, PROGRESS supports TAVR for patients with moderate AS and at-risk features."
Raj Makkar of Cedars-Sinai, the trial's national principal investigator, said the heart can already be under strain at the moderate stage. For selected patients with at-risk features, he said, treating the valve earlier can reduce heart failure events before the narrowing becomes severe.
Pinak Shah of Mass General Brigham, speaking at the TCT press conference, called it a "truly practice-changing study." At the same session Généreux said: "This is going to be a turning point in the way that we see patients with moderate aortic stenosis."
The caution
Not everyone is ready to rewrite the playbook. Catherine Otto, MD, wrote in an accompanying editorial that "TAVR is not appropriate for most adults with moderate [AS]." She said the findings suggest it "may be considered in selected older patients with coexisting conditions at high risk of adverse outcomes when other treatment approaches are not effective."
The enrolled population was selected for risk. 72% had at least two at-risk features, 40% had three or more, and 35.5% presented with severe symptoms, according to Généreux.
A separate registry analysis by Généreux and colleagues, published in JACC, found that moderate aortic stenosis patients outnumber severe patients by nearly 2:1. Généreux said it may help show how far the PROGRESS results can be generalized to the broader moderate-AS population.
Who paid for it
PROGRESS was funded by Edwards Lifesciences, which makes the balloon-expandable Sapien 3 valve used in the TAVR arm. The company's earlier EARLY TAVR trial was also funded by Edwards.
A manufacturer-funded trial can still be a sound trial. It also means the company that stands to gain from a larger pool of eligible patients paid for the evidence that would enlarge it.
What changes, and what doesn't
Current guidelines call for an echocardiogram every one to two years in moderate disease. They recommend valve replacement once the stenosis becomes severe or another surgical indication appears. Aortic stenosis affects more than 3% of adults 65 and older.
Nothing in the guidelines has changed yet. The trial has follow-up planned out to 10 years, which will show whether the two-year gap holds and how a TAVR now affects the need for repeat procedures later. Généreux has said he believes the data show the "optimal timing" for intervention, but Otto's editorial leaves open how far beyond high-risk patients that conclusion can stretch.
Sources used for this briefing
7 links from 7 independent newsrooms (syndicated copies of the same report count once)
These are the sources it draws on, linked so you can verify.


